

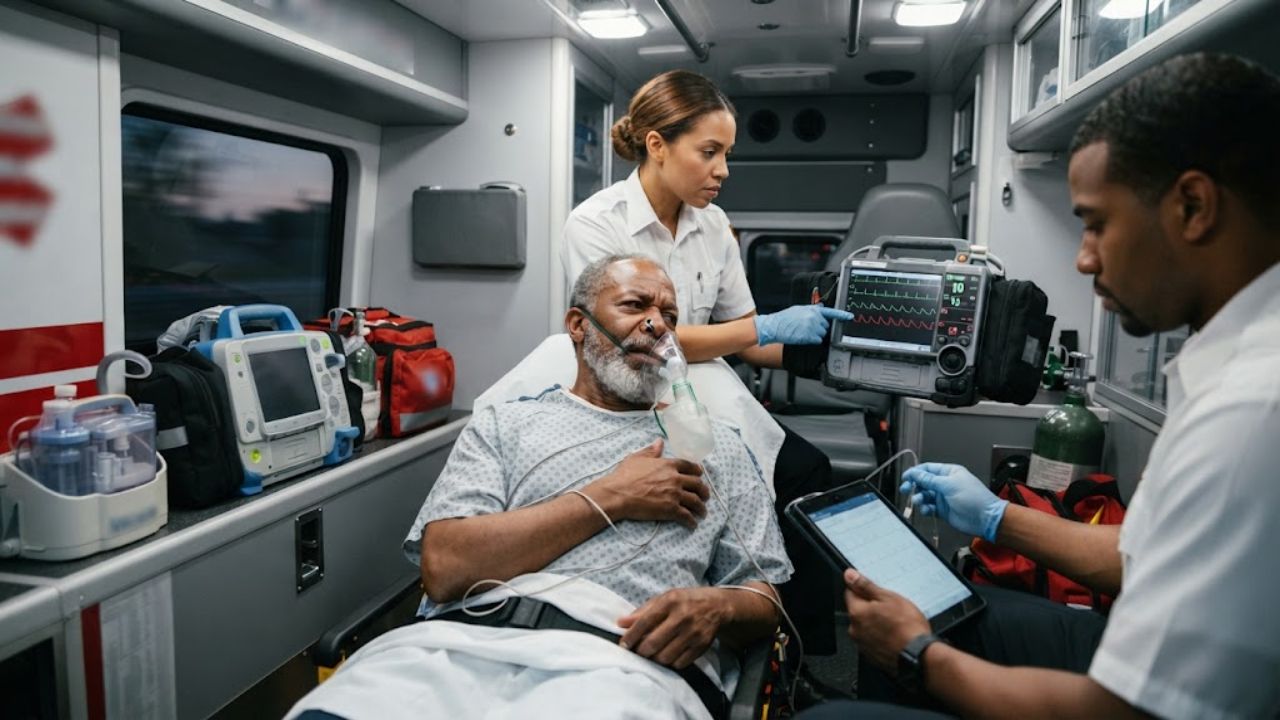
A 75-year-old man with sudden crushing chest pain was in the back of an ambulance when the cardiac monitor caught him going into ventricular tachycardia. Intravenous amiodarone had been drawn up and was about to be administered. Then the ambulance crossed a speed bump at 5 miles per hour, and the jolt put him back into sinus rhythm before the drug did. His only recollection of the journey was how bumpy the ride had been.
Five Miles an Hour, One Jolt, One Rhythm Change
The case appeared in 2006 in the journal Heart under a title that only works in British English: a case of sleeping PC cardioversion. A sleeping policeman is a speed bump.
The sequence is documented on the monitor strips published with the report. The patient developed sudden-onset central crushing chest pain at rest and was brought in by ambulance. Cardiac monitoring during transport captured the onset of his ventricular tachycardia, which was asymptomatic. The amiodarone was prepared. The ambulance went over the bump. He converted. On arrival at the hospital, he was in sinus rhythm and was transferred to coronary care for monitoring.
Ventricular tachycardia in a 75-year-old with crushing chest pain is not a curiosity. It is a rhythm that can deteriorate in a patient who was very likely having a heart attack. What makes the case publishable is that the intervention which ended it was not an intervention at all.
A Precordial Thump by Accident
There is a physiological account, and it is not exotic.
A blow to the chest, delivered with the right energy at the right moment in the cardiac cycle, can depolarize enough heart muscle to interrupt a re-entrant rhythm. Clinicians know this as the precordial thump, and the authors of the Heart report put its electrical output at 2 to 5 joules. Cough-induced and Valsalva-induced cardioversion have also been described.
The proposed explanation for the speed bump is that kinetic energy from the jolt, transmitted through the body of a supine patient, delivered roughly the equivalent of that thump. Timing is the whole story. The same jolt at the wrong instant does nothing, or worse. That is why nobody has ever proposed the speed bump as a treatment, and why the literature treats these reports as illustrations of physiology rather than as options.
A Rectal Thermometer, a Doorframe, and a Farmer with a Shotgun
The speed bump is not alone, and it took an editorial to make that clear. In January 2024, cardiologists writing in Oxford Medical Case Reports assembled the accidental-cardioversion literature into a single table of seven published examples, spanning 1988 to 2023, after a new case crossed their desk.
That case involved a rectal thermometer, which inadvertently converted a 54-year-old patient with stable AVNRT, a form of supraventricular tachycardia. Unusually, it proved reproducible in the same patient, which mattered because conventional approaches were contraindicated for him. The authors attributed it to stimulation of parasympathetic nerve fibers in the rectum, a mechanism that explains why it was neither random nor a one-off. A 2010 report had similarly described atrial fibrillation converting to sinus rhythm in a 29-year-old man during a digital rectal examination, with the patient still asymptomatic three months later.
The rest of the table is a catalogue of coincidence. In 2008, a patient’s hospital bed struck a doorframe on the way to an elective cardioversion for atrial fibrillation, accomplishing the intended procedure before any shock was delivered. In 2006, a man who had refused electrical cardioversion because he did not want sedation hit a mains cable with a drill during home DIY, took a 240-joule shock, converted to sinus rhythm, and was still in it ten weeks later.
The entry the editorialists single out dates to a 1988 letter in the BMJ describing a farmer from Craigavon, Northern Ireland, who had built his own escalating protocol for his permanent junctional reciprocating tachycardia. He began by jumping off a barrel and thumping his feet hard on the ground. If that failed, he climbed a ladder and jumped from higher. If that failed, he fired a 12-bore shotgun. Later he found that jumping into a very cold bath worked. As a last resort, he would grasp a 6-volt electric cattle fence while wearing hob-nailed boots.
The Case That Shows Why Nobody Should Try This
Buried in the same table is the reason this is not just an amusing collection.
In 2018, clinicians reported an 84-year-old man with atrial fibrillation whose rhythm reverted to sinus temporarily when his potassium reached 8.1 millimoles per liter, returning to atrial fibrillation days later once the level normalized. He was not anticoagulated during that transition. He went on to develop an arterial blood clot in his lower limb.
That is the mechanism people forget. Converting atrial fibrillation to sinus rhythm is not automatically good news. Rhythm changes in a patient who is not anticoagulated carry a real risk of dislodging a clot, which is why planned cardioversion is preceded by anticoagulation and imaging decisions. An accidental conversion skips all of that.
The editorial’s own conclusion is measured. While these mechanisms can be explained through existing physiology, its authors write that attempting to replicate the techniques may not be advisable, and they say plainly that they would not feel comfortable recommending a trial of colliding with a wall before offering definitive treatment. Standard care for these rhythms follows established protocols, including European Society of Cardiology guidance on supraventricular tachycardia.
What the collection does argue for is attention. Each of these cases exists because somebody was watching a monitor at the moment something odd happened and thought it was worth writing down. Anyone with a known arrhythmia should follow the plan their cardiology team has set, and new palpitations with chest pain, fainting, or breathlessness need emergency assessment, not a speed bump.
Key Questions Answered
What happened to the patient in the ambulance?
A 75-year-old man with sudden crushing chest pain went into asymptomatic ventricular tachycardia during transport. Intravenous amiodarone was about to be given when the ambulance crossed a speed bump at 5 miles per hour, and the jolt converted him to sinus rhythm.
How could a bump in the road change a heart rhythm?
The proposed explanation is that kinetic energy from the jolt delivered roughly the energy of a precordial thump, a chest blow of about 2 to 5 joules that can interrupt a re-entrant rhythm if it lands at the right moment in the cardiac cycle.
How often does accidental cardioversion happen?
It is rare and reported only as isolated cases. A 2024 editorial assembled seven published examples spanning 1988 to 2023.
What other accidental causes have been reported?
A rectal thermometer, a digital rectal examination, a hospital bed striking a doorframe, an electric shock from a mains cable during home DIY, severe high potassium, and a farmer’s self-devised routine involving jumps, a shotgun, cold water, and an electric cattle fence.
Can an unplanned rhythm conversion be harmful?
Yes. In one reported case, an 84-year-old man whose atrial fibrillation reverted during severe high potassium was not anticoagulated at the time and later developed an arterial clot in his leg.


